Recent Updates Toggle Comment Threads | Keyboard Shortcuts
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
S.H.I.T. happens

_______________________________________________________________________________________________________________

_______________________________________________________________________________________________________________

_______________________________________________________________________________________________________________
-
Juri Katchanov
ICU

A
ABC of Intensive Care
https://vigilant.school.blog/2025/05/01/abc-of-the-intensive-care-bmj-1999/
Analgesia and sedation
https://vigilant.school.blog/2024/08/13/analgesia-and-sedation-in-the-icu/
Anticoagulation
Argatroban
https://vigilant.school.blog/2025/01/04/argatroban/
Heparin
https://vigilant.school.blog/2025/01/04/uhf-heparin-heparin-pseudoresistancy/
HIT
https://vigilant.school.blog/2025/01/04/hit-hit-2-hitt-hitts/
ARDS
https://vigilant.school.blog/2024/09/10/ards/
Arterial line
https://vigilant.school.blog/2025/09/02/arterial-line/
Aspergillosis
https://vigilant.school.blog/2024/09/10/invasive-pulmonary-aspergillosis-in-the-icu/
B
Bronchoscopy
https://vigilant.school.blog/2025/09/08/bronchoscopy/
C
CDI C.diff infection
https://vigilant.school.blog/2025/12/22/c-diff-infection/
Central venous lines
https://vigilant.school.blog/2024/03/15/mental-roadmap-to-cvc/
D
E
vvECMO
Alarm: low flow
https://vigilant.school.blog/2025/05/01/ecmo-alarms-low-flow/
Pressures
https://vigilant.school.blog/2025/09/10/vvecmo-pressures/
Priming
https://vigilant.school.blog/2020/07/29/novolung-priming-ecmo/
Anschluss
https://vigilant.school.blog/2021/08/15/vvecmo-anschluss/
Hypoxemia on vvECMO
https://vigilant.school.blog/2025/04/01/hypoxemia-on-vvecmo/
Hypercapnia on vvECMO
https://vigilant.school.blog/2025/02/01/hypercapnia-on-vvecmo/
ECMO pearls
https://vigilant.school.blog/2005/10/22/pearls-ecmo/
F
Fever
https://vigilant.school.blog/2016/06/06/work-up-elevated-temperature-in-the-icu/
https://vigilant.school.blog/2016/07/06/non-infectious-fever-in-the-icu/
G
H
Hepatorenal
https://vigilant.school.blog/category/kidney-injury/hepatorenal/
HIT
https://vigilant.school.blog/2025/01/04/hit-hit-2-hitt-hitts/
I
Impella
https://vigilant.school.blog/2025/08/23/impella/
Induction
https://vigilant.school.blog/2026/02/04/very-smooth-induction-asa-2/
Intubation
https://vigilant.school.blog/2024/12/02/mental-roadmap-to-intubation/
VL
https://vigilant.school.blog/2024/12/02/video-laryngoscopy-vl/
J
K
KetanestS
https://vigilant.school.blog/2024/03/03/s-ketamin-ketamins-esketamin-ketanests/
L
Levosimedan
https://vigilant.school.blog/2025/08/23/levosimedan/
Lidocain
https://vigilant.school.blog/2026/05/04/lidocain-als-co-analgetikum/
M
Methylene Blue
https://vigilant.school.blog/2026/01/07/methylene-blue/
N
NeuroICUs in MUC
https://vigilant.school.blog/2025/01/31/neurologische-icus-in-munchen/
Neuromuscular blockade
https://vigilant.school.blog/2024/04/11/mental-roadmap-to-neuromuscular-blocking-agents-nmb-nmba/
NOMI
https://vigilant.school.blog/2026/02/19/nomi/
O
OFA
https://vigilant.school.blog/2026/05/04/ofa/
Ö
P
Pacemakers
temporary intravenous pacing
https://vigilant.school.blog/2025/08/05/pacemaker-settings/
permanent pacemakers
https://vigilant.school.blog/2024/12/12/schrittmacher-notfalle/
PDK
https://vigilant.school.blog/2025/10/27/pdk-markierungen/
Perfusoren
https://vigilant.school.blog/2025/11/06/perfusoren-barmherzige-bruder/
PESO
https://vigilant.school.blog/2024/09/10/peso/
PH pulmonary hypertension
https://vigilant.school.blog/2020/01/15/pulmonary-hypertension/
PiCCO
https://vigilant.school.blog/2024/11/13/mental-roadmap-to-picco/
Postoperative care
https://vigilant.school.blog/2023/11/16/mental-roadmap-to-postoperative-care/
Post-PCI care
https://vigilant.school.blog/2026/02/13/post-pci-care/
PT
https://vigilant.school.blog/2025/09/01/perkutane-dilatative-tracheotomie-pt/
Q
R
Respiration and ventilation
https://vigilant.school.blog/2022/05/11/refractory-hypoxemia/
RSI Notfallnarkose
https://vigilant.school.blog/2026/02/04/rsi-notfallnarkose/
RV failure
https://vigilant.school.blog/2021/12/08/acute-rv-dysfunction-failure/
S
Sepsis
https://vigilant.school.blog/2019/11/28/refractory-septic-shock/
Steroids in the ICU
https://vigilant.school.blog/2014/07/23/steroids-in-the-icu/
T
TOF
https://vigilant.school.blog/2025/08/23/tof/
U
Ü
V
Vasopressors
https://vigilant.school.blog/2024/11/28/vasopressors-as-drips-perfusor/
Ventilation
Crashing ventilated patient
https://vigilant.school.blog/2026/06/03/crashing-ventilated-patient/
W
X
Y
Z
-
Juri Katchanov
Hypercortisolism (Cushing)

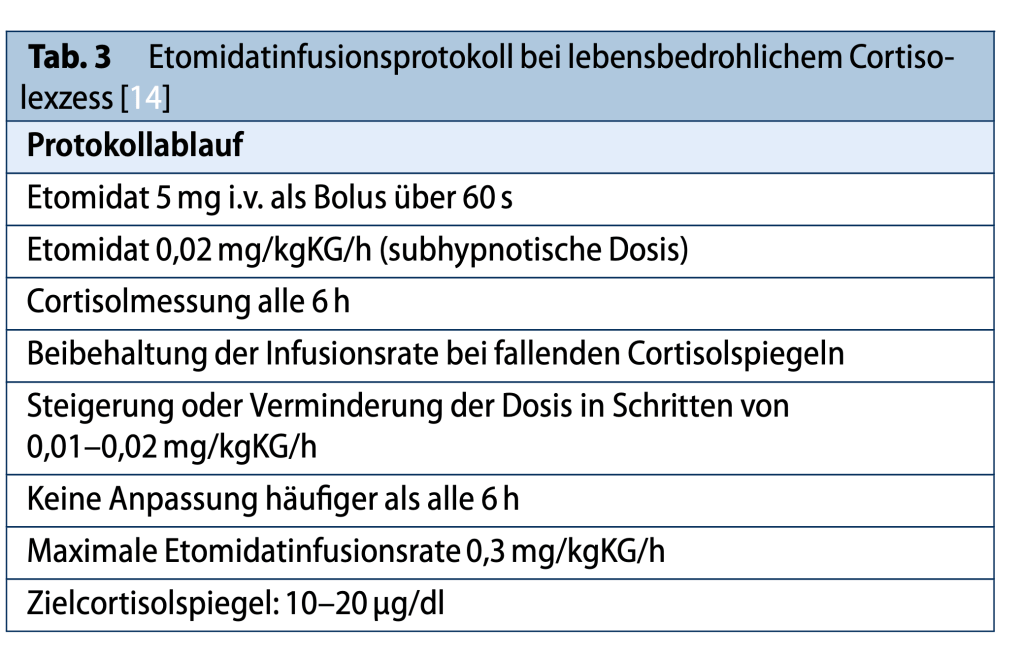
ACTH im Labor Becker (EDTA, sofort abzentrifugieren und einfrieren)
https://www.labor-becker.de/leistungsverzeichnis/3664/acth
Cortisol: Serum
https://www.labor-becker.de/leistungsverzeichnis/3872/cortisol
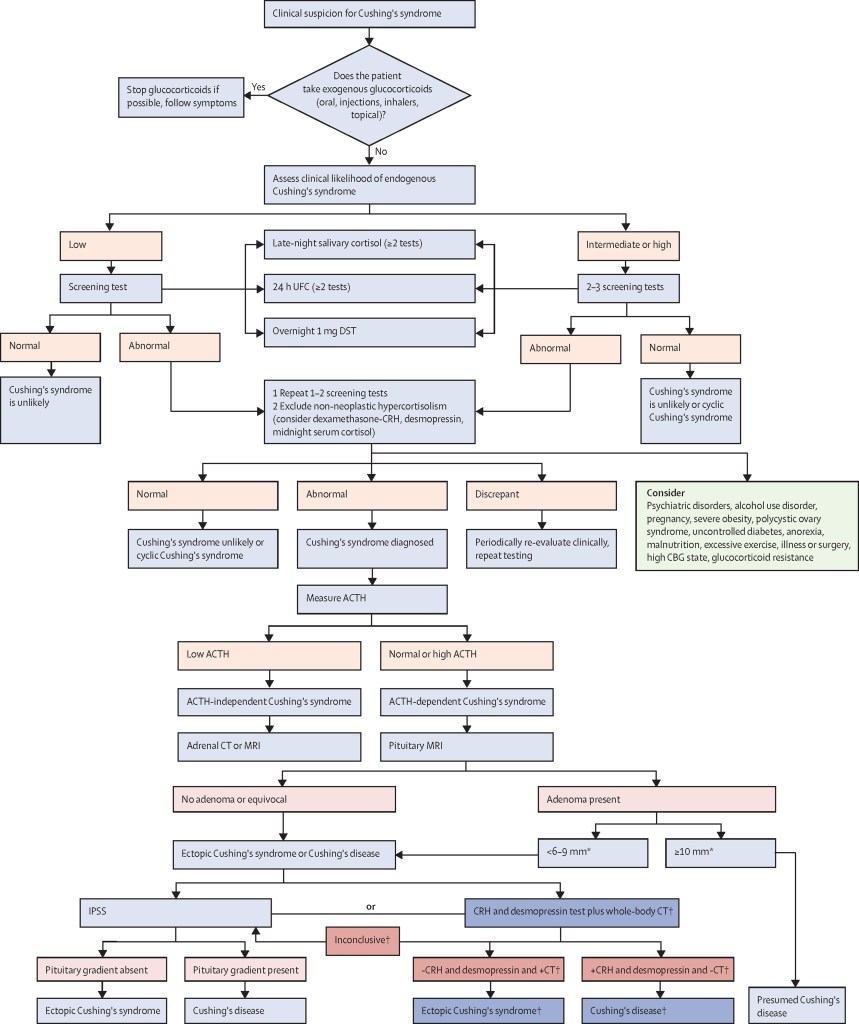
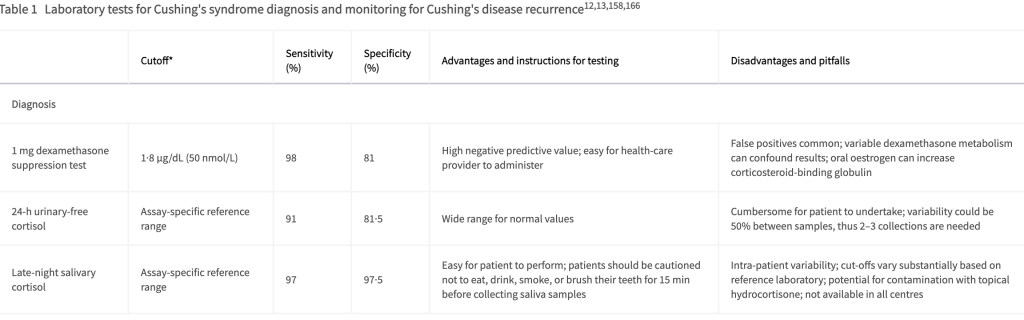
Screenshot 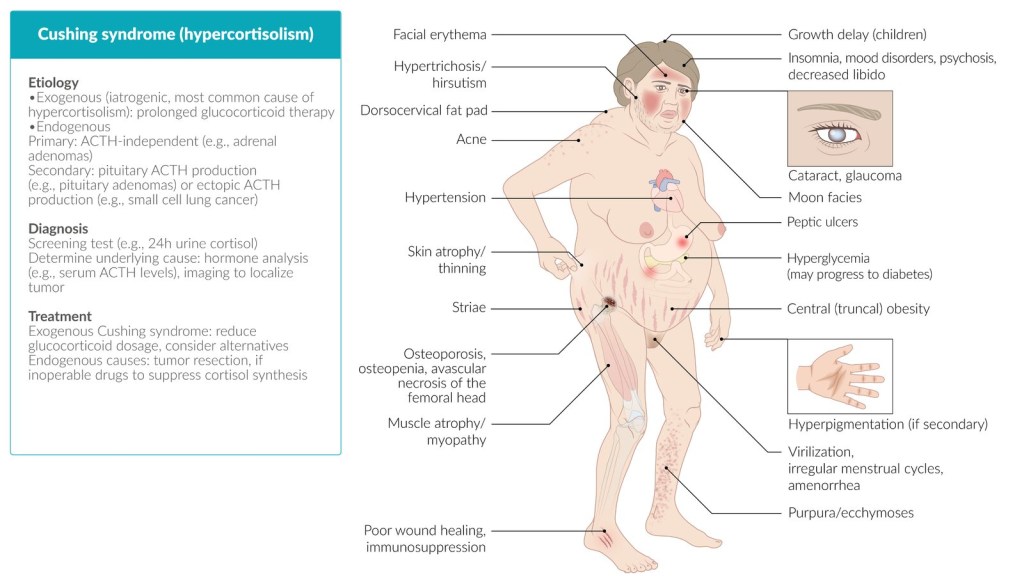
-
Juri Katchanov
thyroid storm, thyreotoxic crisis

Burch-Wartofsky:
https://www.mdcalc.com/calc/3816/burch-wartofsky-point-scale-bwps-thyrotoxicosis

Fachinfo
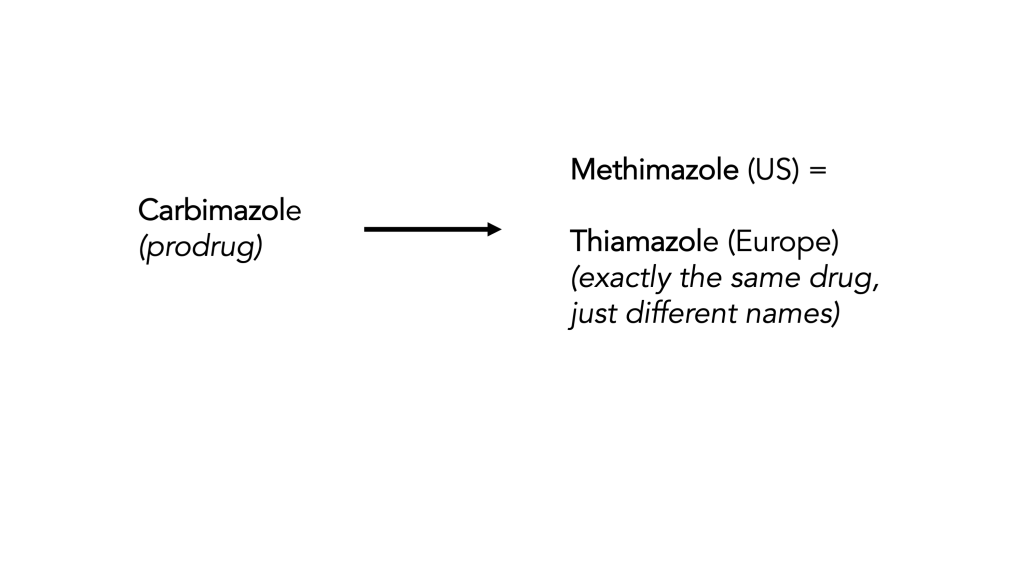
Thiamazol 40 mg inject. Henning
Die Therapie des durch eine schwere Überfunktion bedingten Komazustandes (thyreotoxische Krise) erfolgt neben anderen allgemein üblichen Maßnahmen der Notfallmedizin (Intensivpflege, Infektbekämpfung, Betarezeptorenblocker) vor allem mit einer intravenösen Gabe von anfänglich 2 Ampullen Thiamazol 40 mg inject. Henning.
Anschließend folgt eine Dauerinfusion von 120 bis 240 mg Thiamazol pro 24 Stunden.
In bestimmten Fällen kann eine Plasmapherese oder die Thyreoidektomie (z. B. bei Iodkontamination) erforderlich werden.
In bestimmten Fällen, in denen die orale Behandlung nicht angebracht ist (mangelnde Resorption, unregelmäßige Tabletteneinnahme, Zustand nach einer Operation etc.), kann Thiamazol 40 mg inject. Henning in den einer oralen Medikation entsprechenden Dosen zwischen 10 und 40 mg pro Tag, je nach Schweregrad der Erkrankung, verabreicht werden.https://www.fachinfo.de/fi/pdf/002077/thiamazol-henning-r
-
Juri Katchanov
hyperthyreosis
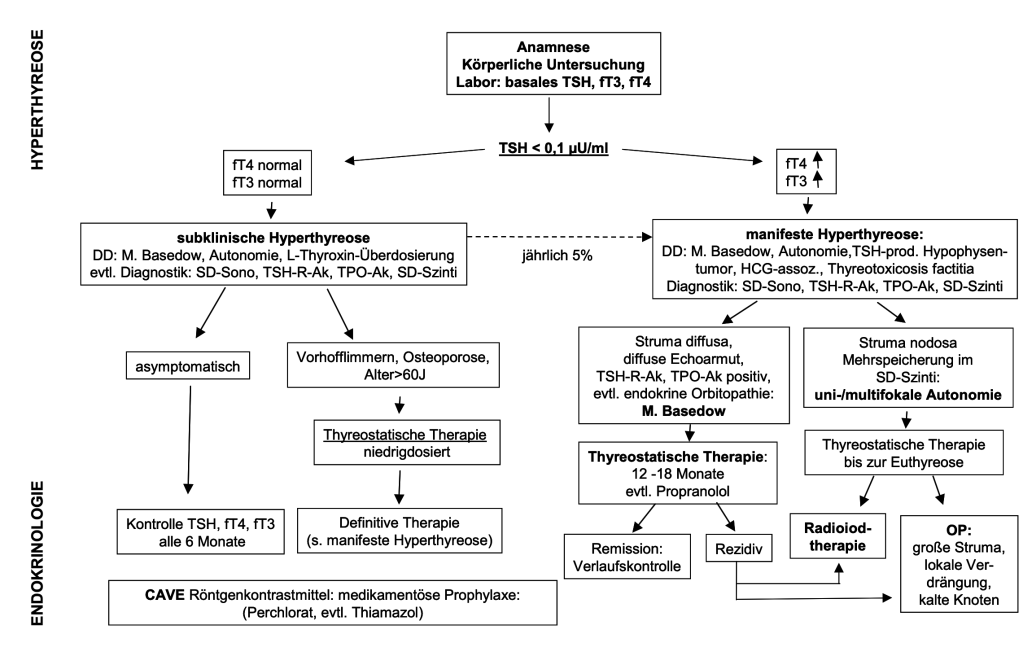
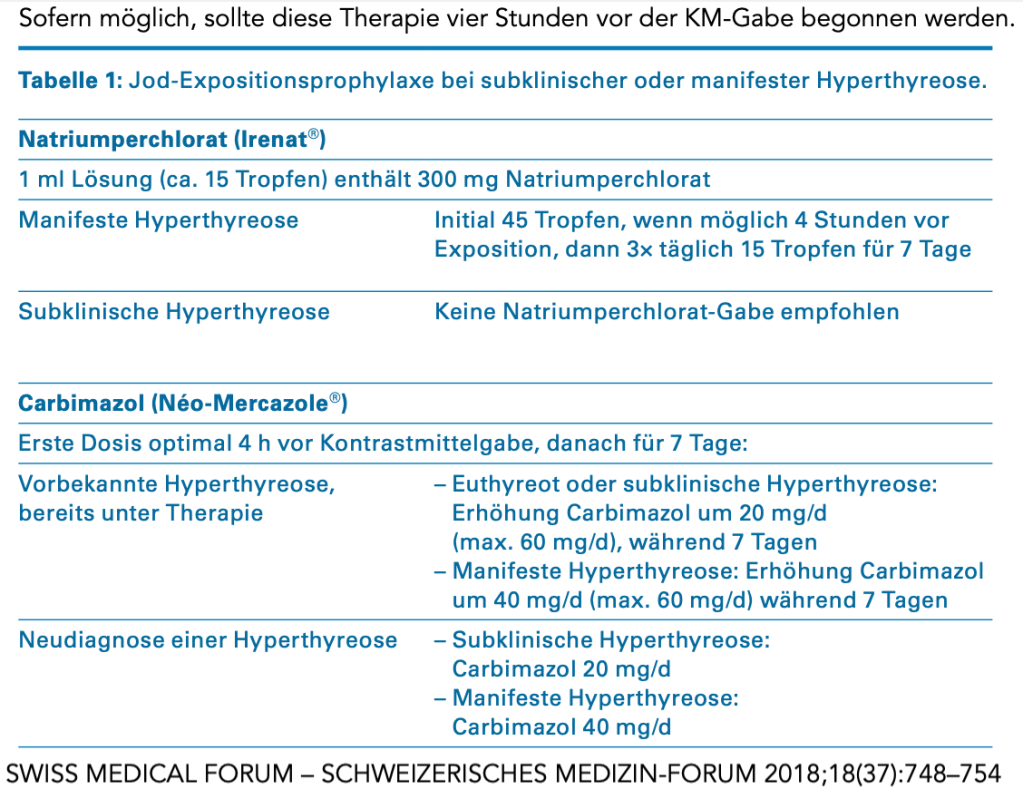
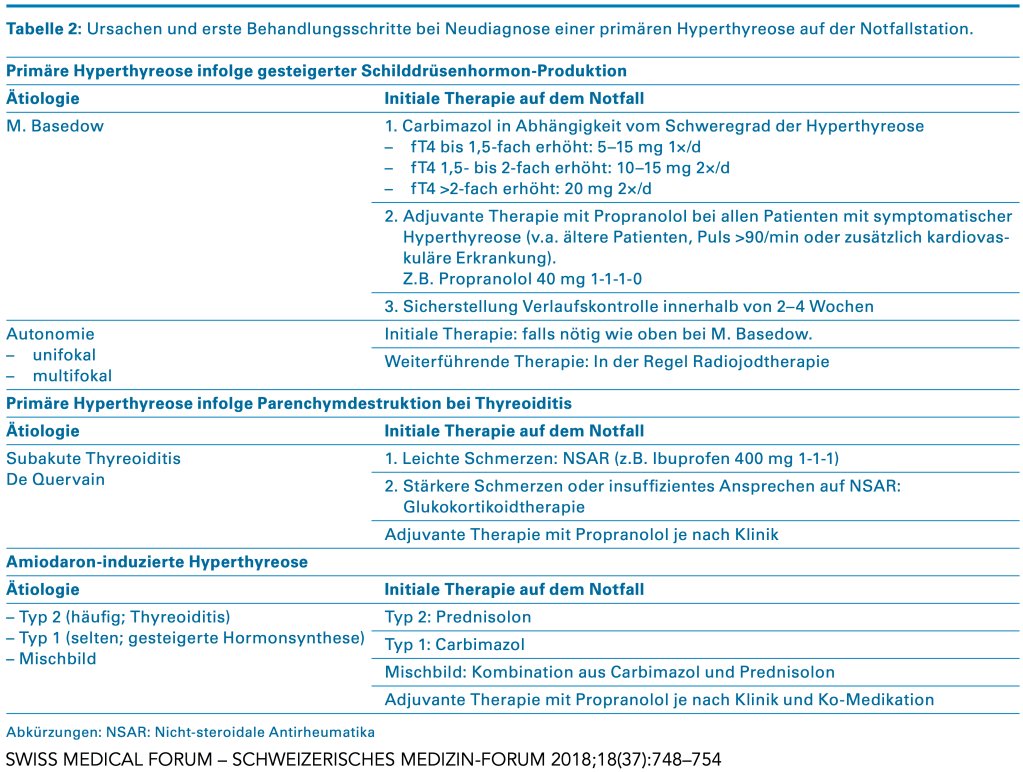
Bei einer manifesten Hyperthyreose ist die Therapieindikation klar gegeben.Die initiale Therapieerfolgt medikamentös mit Thyreostatika vom Thioamidtyp (Thiamazol und
Carbimazol) oder mit Propylthiouracil (PTU). Carbimazol und Thiamazol werden 1-mal
täglich verabreicht, wohingegen PTU aufgrund der kürzeren Halbwertszeit 2- bis 3-mal täglich
gegeben wird. Die initiale Dosis richtet sich unter anderem nach der Einschätzung des Schwere-
grads der Hyperthyreose, dem Schilddrüsenvolumen und dem Vorliegen einer Jodbelastung. In
Abhängigkeit vom Ausmaß der Hyperthyreose sind folgende Erstdosierungen gebräuchlich:
Thiamazol 10–30 mg täglich
Carbimazol 15–45 mg täglich
Hepatitis und Agranulozytose zählen zu den schwersten thyreostatikabedingten Nebenwir-
kungen. Sie treten durchschnittlich in den ersten ein bis eineinhalb Monaten nach Therapiebeginn
auf. Eine 2-wöchentliche Kontrolle des Differenzialblutbilds und der Leberwerte scheint
daher in den ersten 6 Wochen sinnvoll.
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
-
Juri Katchanov
知恵
知恵(ちえ)
Weisheit
σοφία
prudentia, sapientia
prudence, wisdom
jñāna
prajña
la sagesse
la sabiduría

______________________________________________________________________________________________________

______________________________________________________________________________________________________
____________________________________________________________________________________________________
_____________________________________________________________________________________________________
______________________________________________________________________________________________________

_______________________________________________________________________________________________________

________________________________________________________________________________________________________

_________________________________________________________________________________________________________

________________________________________________________________________________________________________ 
_____________________________________________________________________________________________________

________________________________________________________________________________________________________
-
Juri Katchanov
















Reply